
Summary
Despite considerable investment in recruitment strategies for Alzheimer’s disease (AD) clinical trials, relatively little is known about where stakeholders across the recruitment ecosystem agree—or disagree—on the factors that most influence recruitment success. Understanding these perspectives can help identify opportunities for coordinated action and inform future investments in recruitment science.
The Clinical Trial Recruitment Lab (CTRL) at the USC Schaeffer Institute for Public Policy & Government Service interviewed representatives from five stakeholder groups spanning the AD clinical trial ecosystem: academic, commercial, contract research organizations, sponsors and vendors. Analyzing interview responses allowed the team to identify four strategic areas for accelerating recruitment: strengthening trial design and site selection; improving participant identification; aligning funding and operational capacity; and building sustainable recruitment infrastructure.
Continued cross-stakeholder collaboration and knowledge sharing can translate these insights into coordinated action, positioning the field to support more timely, representative and patient-centered AD clinical trial recruitment.
Introduction
After more than 30 years, the first disease-modifying treatments for Alzheimer’s disease (AD) have reached the market, marking a landmark achievement for the field. Yet substantial unmet therapeutic need remains. Current treatments do not halt or reverse disease progression, are approved only for early symptomatic AD—including mild cognitive impairment and mild dementia due to AD—and carry the risk of serious adverse events.[1] Ongoing development of new therapies is essential.
However, persistent recruitment challenges continue to slow AD clinical trials and delay the development of future treatments for people living with AD. Stakeholders across the AD clinical trial ecosystem have implemented a range of strategies to improve recruitment, and some have shown promise.[2] Yet, to date, these efforts have been insufficient to address the scale of the challenge. For example, among the 192 AD clinical trials underway in 2026, most reported difficulties enrolling participants.[3,4] Lasting improvement will require coordinated action across the entire AD clinical trial ecosystem to address the systemic barriers limiting recruitment and trial participation.
To better understand persistent recruitment challenges, the Clinical Trial Recruitment Lab (CTRL) at the USC Schaeffer Institute for Public Policy & Government Service conducted 16 semi-structured interviews with representatives from five stakeholder groups across the AD recruitment ecosystem: academic medical centers, commercial research sites, contract research organizations (CROs), research sponsors, and vendors. The interviews explored barriers, emerging practices and opportunities to improve recruitment. The findings reveal broad areas of consensus while highlighting important differences in how stakeholders experience and prioritize recruitment challenges.
Stakeholder perspectives converged around four strategic areas for accelerating recruitment:
- Strengthen the foundation for recruitment by optimizing protocol design, eligibility criteria and site selection—decisions with the greatest downstream influence on recruitment success
- Improve the recruitment funnel by expanding participant identification, adequately funding pre-screening and adopting new approaches for earlier-stage trials
- Align funding, organizational incentives, and operational capacity across sponsors, sites and healthcare systems to better support recruitment activities
- Invest in sustainable recruitment infrastructure by strengthening community partnerships, expanding the evidence base, and modernizing technology and data systems.
1. Strengthening the Foundation for Recruitment Success
Recruitment Is a Complex, Multi-Stage System—Not a Single Task
Across all five interview groups, recruitment was consistently described as a multi-stage, interconnected process involving participant identification, outreach, pre-screening, engagement, screening, and retention. No single strategy or tool was viewed as sufficient to ensure successful recruitment. Instead, stakeholders emphasized that success depends on coordinated investment across the entire recruitment pathway, use of multiple complementary recruitment approaches and sustained effort across studies.
Protocol Design and Site Selection Are the Highest-Leverage Upstream Decisions
Protocol design and site selection were identified as the decisions with the greatest influence on recruitment success. Because these decisions are made early in trial planning and are often difficult to modify once a study begins, they shape recruitment outcomes throughout the trial.
Overly complex protocols—including burdensome procedures, frequent study visits, and restrictive eligibility criteria—were consistently identified as major drivers of slow enrollment. Site selection likewise determines who will execute the trial and is therefore critical to recruitment success. Key considerations include prior site performance, geographic location, access to diagnostic infrastructure and experience with regulatory requirements. Contract research organizations (CROs) noted that sites with a strong track record generally recruit most reliably, while geography and local infrastructure can constrain recruitment feasibility. In large Phase 3 trials, however, sponsors may need to include less experienced sites to meet enrollment targets, increasing execution risk. Academic and commercial stakeholders also emphasized that strong site leadership and operational support are critical to successful recruitment.
Academic and Commercial Sites Present Fundamental Trade-Offs
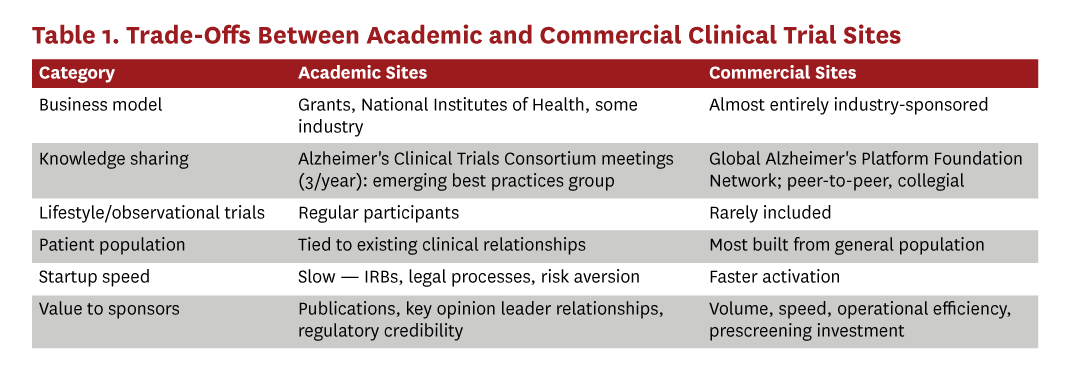
All stakeholder groups described a fundamental trade-off between academic and commercial sites. Commercial sites were consistently viewed as offering greater speed and operational efficiency, whereas academic sites provide access to participants through established relationships, scientific leadership and institutional credibility, but often require more time and resources to initiate and conduct studies (Table 1). Several stakeholders suggested that incorporating resources that streamline and accelerate the site setup process could help address the limitations of academic sites. Sponsors, CROs, and vendors emphasized that both academic and commercial sites play essential roles in AD clinical trials, although commercial sites currently comprise the majority of sites used in many studies.
“I don’t think [recruitment is] ever really solved. It’s not an on/off switch, it’s a dial we turn up.”
– Commercial site
2. Improving the Recruitment Funnel
Participant Identification and Funnel Leakage Are the Primary Bottlenecks
All five stakeholder groups identified participant identification and early recruitment funnel attrition as the most significant structural challenges to AD clinical trial recruitment, particularly as studies increasingly target earlier-stage and pre-symptomatic populations. Stakeholders emphasized that the gap between the theoretical pool of eligible participants and those who ultimately enroll remains substantial. Existing approaches—including participant registries, ad hoc electronic medical record (EMR) queries and referral networks—have not been sufficient to close this gap.
Stakeholders also noted that policy can create unintended barriers to participation. For example, one sponsor described how compensation for trial participation, even when approved by an Institutional Review Board (IRB), may affect participants’ tax liability or eligibility for public programs, potentially discouraging enrollment.
Pre-Screening Is High-Value but Systemically Underfunded
Commercial sites, CROs, and sponsors identified continuous pre-screening as one of the highest-leverage strategies for reducing screen failure rates and improving recruitment efficiency. By identifying likely eligible participants before formal screening begins, pre-screening can improve enrollment performance and reduce costs throughout the recruitment process.
Despite its value, pre-screening is rarely reimbursed by sponsors and is typically funded by sites outside the scope of standard trial operations. Stakeholders noted that this model disadvantages newer and smaller sites, particularly those serving underserved communities, which often lack the resources to invest in ongoing pre-screening infrastructure. Vendors also observed that many legacy screening tools lack the sensitivity needed to identify individuals in the earliest stages of AD.
Centralized Recruitment Vendors and Registries Can Have Variable Performance
Commercial sites, CROs, sponsors, and vendors agreed that national registries consistently underdeliver and many external centralized recruitment tactics fail to perform, generating low conversion rates, duplicated referrals, poor participant-study matching and uncertain return on investment.
Stakeholders emphasized that identifying potential participants through centralized approaches does not reliably translate into enrollment at the site level. Academic sites reported using registries but noted that their effectiveness is highly dependent on context, target population, and study design. One site observed that registries tend to perform better in prevention studies than in trials enrolling participants with mild cognitive impairment or symptomatic AD.
Earlier-Stage Trials Require New Approaches to Participant Identification and Recruitment
Academic sites and sponsors explicitly described a fundamental shift in the future of AD clinical trials: Studies are increasingly targeting pre-symptomatic and primary prevention populations, incorporating decentralized and remote assessments, and requiring recruitment at a scale that exceeds current infrastructure. CROs and vendors similarly noted that existing recruitment tools and approaches are not well suited to support this transition. Collectively, stakeholders emphasized that adapting to this shift will require systemic changes to how participants are identified, engaged and enrolled.
“There are so many people with Alzheimer’s—[but] we can’t find them.”
– Sponsor
“We used the EMR to send out postcards … we were completely unfamiliar with this style of recruiting … we weren’t meeting our numbers. Then we tried direct mail using Medicare lists and met our recruitment goal.”
– Academic site
“We encourage our customers to think about a stepwise approach to screening—that would help to exclude patients because screen failure rates are anywhere between 50 and 80-plus percent.”
– CRO
3. Aligning Funding and Operational Capacity
Recruitment Is Structurally Underfunded—Sponsors and Sites Are Misaligned
Academic, commercial, CRO, and vendor representatives independently described a fundamental mismatch between sponsors’ centralized, study-specific funding models and the sustained, locally driven, relationship-based recruitment efforts needed to successfully enroll participants. These local efforts require significant up-front investment despite uncertain participant flow.
Stakeholders reported that this misalignment leaves site-level recruitment consistently under-resourced, shifts disproportionate financial risk to sites, and weakens incentives to invest in long-term recruitment capacity. Because local, relationship-based recruitment activities are more difficult to measure than centralized recruitment efforts, they are also more difficult to justify and fund. As a result, high-performing sites often finance their own recruitment infrastructure, while smaller sites frequently lack the resources to do so.
The Gap Between Clinical Care and Clinical Research Remains an Under-Addressed Bottleneck
Commercial sites, sponsors, and vendors identified physicians as critical gatekeepers who can either facilitate or impede clinical trial participation. Stakeholders noted that physicians often lack the time, awareness or confidence to discuss clinical trials with patients and, in some cases, may actively discourage participation.
Stakeholders viewed this disconnect between routine clinical care and clinical research as a persistent structural barrier that remains largely unaddressed by current recruitment models. Vendors and CROs also highlighted the challenges of identifying and referring eligible patients from healthcare settings that are not integrated into the clinical trial ecosystem.
“I don’t know a site very well, and they ask me [for funds] … to go run their recruitment tactics, and I have to demonstrate that it’s going to be a value-added endeavor.”
– CRO
“For a lot of doctors, it’s not that they’re averse to clinical trials—doctors don’t have time in their busy practices. It opens a Pandora’s box.”
– Commercial site
4. Building Sustainable Recruitment Infrastructure
Community- and Relationship-Based Engagement Drives Durable Recruitment
Academic, commercial and sponsor stakeholders consistently identified trust-based, community-embedded engagement as the most effective long-term strategy for AD clinical trial recruitment. Stakeholders emphasized that most participants are not ready to enroll when first approached. Instead, enrollment is built through sustained relationships developed over time through community presence, trusted referrals and ongoing engagement. Building and maintaining these long-term trust networks was viewed as essential for durable recruitment success.
A Striking Gap Exists Between Recruitment Knowledge and Published Evidence
All five stakeholder groups independently identified the same structural challenge: Much of the field’s recruitment knowledge remains tacit, experience-based, and neither systematically captured nor widely shared. Stakeholders noted that published evidence is underutilized in practice, lessons learned are rarely transferred across organizations and effective approaches are often rediscovered rather than built upon.
Although participants across stakeholder groups expressed a willingness to share recruitment insights, they also noted the lack of practical mechanisms to do so. Vendors further emphasized that gaps in recruitment data limit the ability to evaluate the effectiveness of different recruitment strategies. Collectively, stakeholders identified a shared, accessible knowledge infrastructure—one that captures recruitment evidence and translates it into role-specific, actionable guidance—as a critical unmet need.
Technology and Data Systems Are Fragmented and Not Yet Ready to Scale
All stakeholders recognized the potential of emerging technologies—including artificial intelligence (AI), EMR-based participant identification, predictive analytics and integrated data systems—to improve recruitment. However, they consistently described current technologies as fragmented, poorly integrated and not yet capable of supporting recruitment at scale.
Stakeholders also noted that site-level data systems remain largely manual and disconnected, limiting visibility into the recruitment funnel, hindering performance measurement and constraining continuous improvement. They emphasized the need for better system integration, standardized recruitment metrics and more robust data infrastructure to fully realize the potential of these technologies.
“It’s important to actually embed in communities and understand how to ensure that we are a trusted voice.”
– Sponsor
“Pre-screening data is important—how many patients did we have to screen … I don’t have that data.”
– CRO
“There is so much [recruitment] experience that is not captured anywhere.”
– Sponsor
“We’re just winging it on how to maximize the use of the EMR.”
– Academic site
“None of the software is really ideal if we really want to understand the recruitment pipeline.”
– Commercial site
Recruitment Barriers and Corresponding Solutions
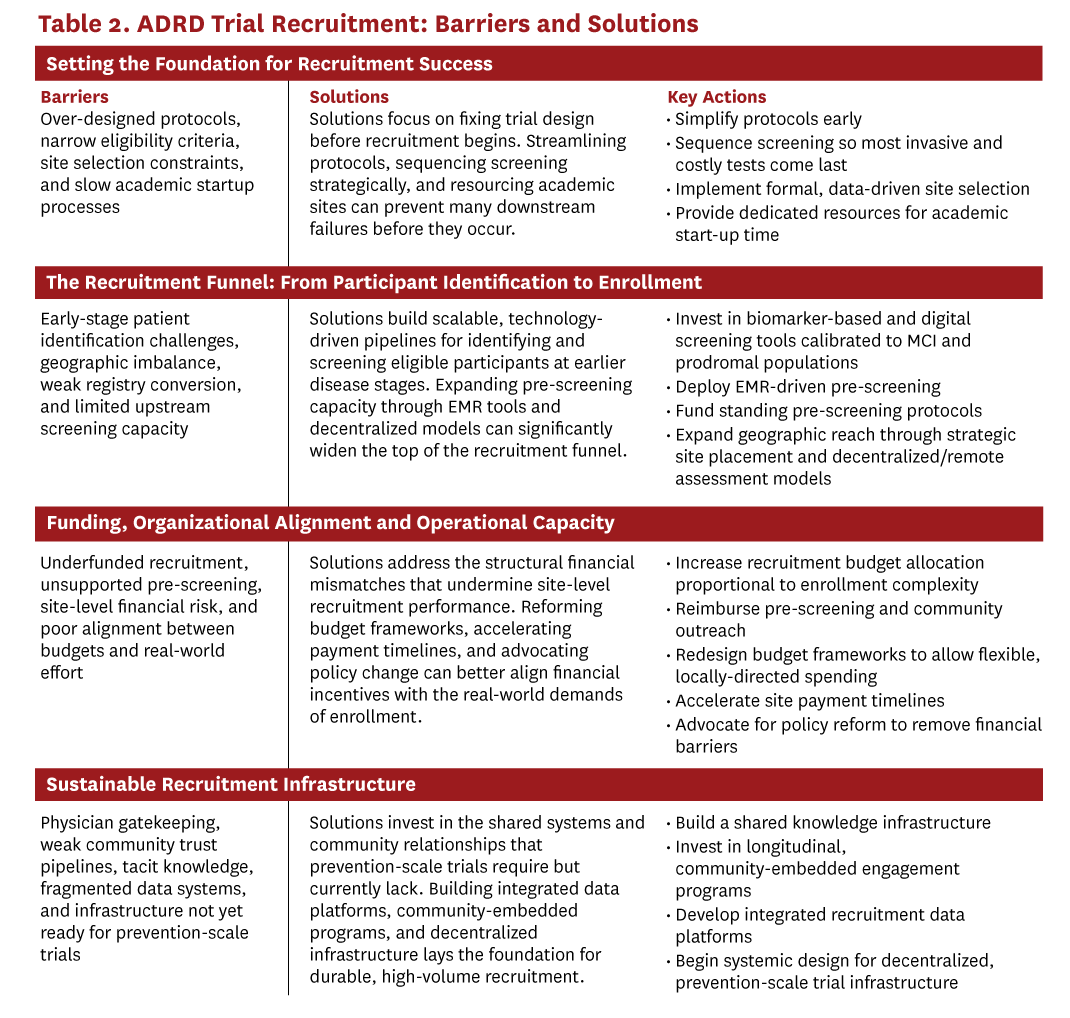
Recruitment barriers are not isolated challenges occurring at a single point in the process, but interconnected constraints that begin with upstream trial design and site selection, extend through participant identification and recruitment funnel management, and are reinforced by limitations in funding, organizational alignment, community engagement, knowledge sharing, and technology infrastructure. Across each of the four strategic areas, stakeholders also identified opportunities to address these barriers, highlighting practical strategies for strengthening AD clinical trial recruitment (Table 2).
Conclusion
Improving AD clinical trial recruitment will require coordinated actions across four strategic areas: strengthening trial design and site selection, improving participant identification, aligning funding and operational incentives, and investing in sustainable recruitment infrastructure. Throughout the interviews, stakeholders revealed both broad areas of consensus and important differences shaped by their role, incentives, and operational constraints.
Stakeholders consistently emphasized distinct priorities:
- Academic sites highlighted the importance of longitudinal community engagement and trust-based relationships.
- Commercial sites prioritized operational infrastructure and portfolio management.
- CROs focused on site capability and measurable recruitment performance.
- Sponsors identified protocol design and site selection as the highest-leverage determinants of recruitment success.
- Vendors emphasized the growing mismatch between participant identification tools designed for prevalent, later-stage disease, and the field’s shift toward earlier-stage and prevention trials, while also highlighting the lack of sponsor support for pre-screening activities.
These findings demonstrate that recruitment challenges are not monolithic. Rather, they vary according to stakeholders’ responsibilities and positions within the recruitment ecosystem. For example, commercial sites, CROs, sponsors and vendors consistently reported low recruitment conversion from centralized vendors and registries, whereas academic sites described registries as valuable when strategically aligned with the target population and integrated into patient-centered care.
Understanding where stakeholder perspectives converge—and where they diverge—is essential for designing effective solutions. Areas of broad agreement, such as improving participant identification, strengthening community engagement and expanding mechanisms for shared learning, represent opportunities for coordinated investment. At the same time, successful implementation will require strategies that account for stakeholder-specific constraints. For example, continuous pre-screening may improve recruitment efficiency but is unlikely to be widely adopted unless supported by sustainable funding. Similarly, site-level investments may be difficult for sponsors and CROs to justify without stronger evidence of recruitment performance and return on investment.
Ultimately, improving AD clinical trial recruitment will require coordinated action across the recruitment ecosystem. Progress will depend on aligning trial design, operational capacity, funding models, patient-centered engagement, technology, and shared evidence to support a more efficient, equitable and sustainable recruitment system.
The value of this work lies in identifying where stakeholder perspectives align, where they differ, and where important gaps remain. Continued cross-stakeholder collaboration and knowledge sharing can help translate these insights into coordinated action, positioning the field to support more timely, representative and patient-centered AD clinical trial recruitment.
References
- Kovacik, A., K. Vandergriff, C. Clevenger and B. Jarrett. (2025). An Update of the Treatment Landscape for Alzheimer’s Disease: From symptomatic Treatments to the Emergency of Amyloid-Targeting Therapies. Sage Open Aging 11. https://doi.org/10.1177/30495334251376614.
- Jacobson, M., C. Deuschle, D. Peneva, A. Nuo-Yi Wang, C. Roache, M. Walsh, P. Barkman Ferrell, M.-A. Manetas, R. Raman, P. Aisen and D. Goldman. (2026). Evaluating Evidence-Based Recruitment Strategies for Alzheimer’s Disease and Related Dementias Clinical Trial Research: A Literature Review. Journal of Prevention of Alzheimer’s Disease, 13 (5): 100532. https://doi.org/10.1016/j.tjpad.2026.100532.
- Aisen, P., D. Peneva, M. A. Manetas, M. Jacobson, D. Goldman, N. Bose, P. Barkman Ferrell, V. K. Vu and Rema Raman. (2025). Advancing the Science of Recruitment for Alzheimer’s Clinical Trials: Challenges and Opportunities. Journal of Prevention of Alzheimer’s Disease, 12 (7): 100230. https://www.sciencedirect.com/science/article/pii/S2274580725001736.
- Cummings, J., Y. Zhou, Y. Yang, K. Zhong, J. Fonseca, A. Leisgang Osse and F. Cheng. (2026). Alzheimer’s Disease Drug Development Pipeline: 2026. Alzheimer’s & Dementia, 12 (2): e70251. https://doi.org/10.1002/trc2.70251.
Supplemental information is available in the PDF version. This issue brief was prepared by Rose Li and Associates, Inc. (RLA), with substantial contributions from Christina Deuschle, Meghan Walsh, and Cat Thomson.


